
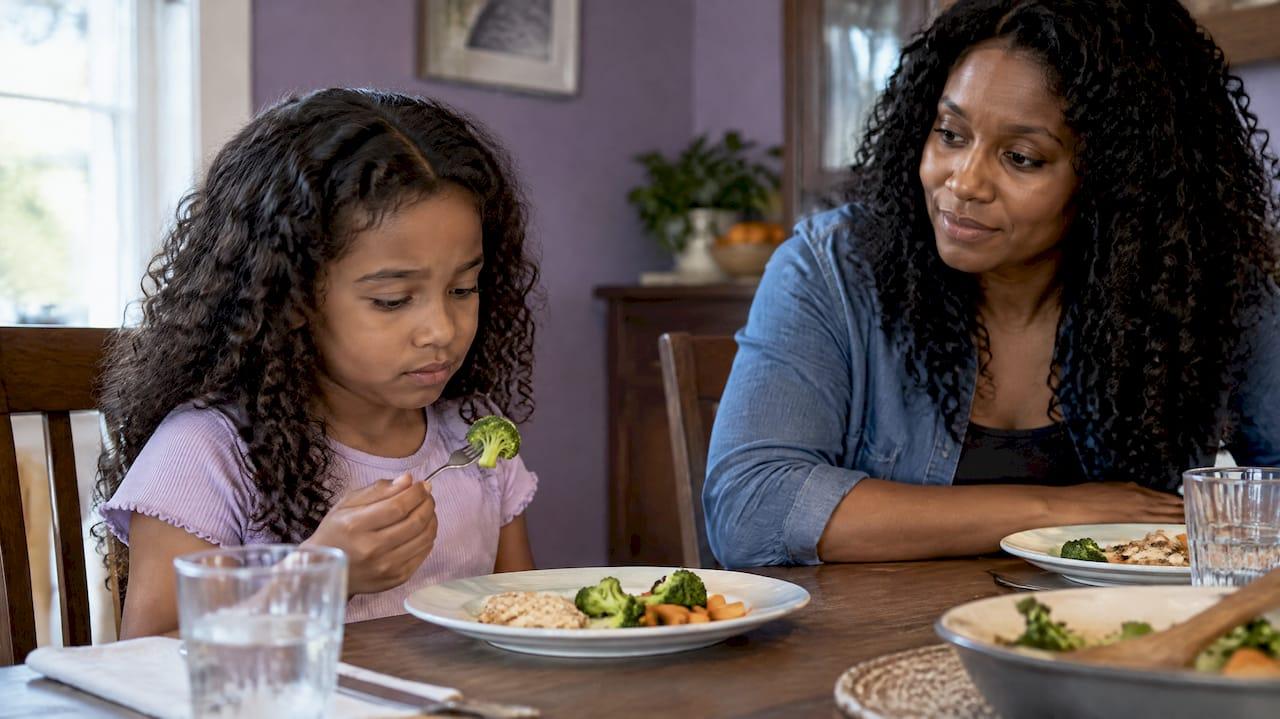
Most picky eaters are going through a normal phase. A problem feeder is a child whose eating is restricted enough, or stressful enough, that they usually need extra support. The clearest clues are how many foods your child accepts, how they react when a new food shows up, and whether whole groups of foods or textures have dropped off the menu. If you are reading this with a knot in your stomach at dinnertime, you are not alone, and there is a lot we can do together.
Below, we walk through the differences, the red flags, what to try at home, and when it is time to call your pediatrician or a feeding therapist.
TL;DR
- Picky eaters usually accept about 30 or more foods and can tolerate a new food on the plate. Problem feeders often accept fewer than 20 and may cry or refuse completely when a new food appears.
- Poor weight gain, low energy, dehydration, gagging or breathing trouble with meals, and heavy caregiver stress are signs to call your child's doctor.
- At home, offer a variety of foods, skip the pressure, and keep meals calm and predictable.
- If your child's diet is shrinking or meals are a daily battle, ask your pediatrician about a feeding evaluation.
- Feeding therapy is designed to find the root cause, not just push your child to eat.
Picky eater or problem feeder: the short answer
The two labels describe different points on a spectrum. Neither one means you did something wrong.
Feeding Matters, a nonprofit focused on pediatric feeding disorder, publishes a side-by-side comparison drawn from the SOS Approach to Feeding. It describes picky eaters as children with a narrower range of foods who still typically eat at least 30 different foods. They can usually tolerate a new food on the plate, even if they only touch or taste it reluctantly, and they still eat from most texture and nutrition groups.
Problem feeders, in the same comparison, tend to eat a much more limited range, often fewer than 20 foods. They may cry, fall apart, or refuse entirely when a new food is presented, and they may refuse whole texture or nutrition categories.

Those numbers are a guide, not a diagnosis. A child who eats 25 foods but is losing foods quickly, or who gags at the sight of anything green, still deserves a closer look. A trained feeding professional looks at the whole picture: growth, medical history, oral-motor skills, sensory responses, and mealtime dynamics.
Side-by-side: what each looks like at the table
| What you notice | Typical picky eater | Possible problem feeder |
|---|---|---|
| Number of accepted foods | About 30 or more | Often fewer than 20 |
| New food on the plate | Can tolerate it, may touch or taste | Cries, melts down, or refuses completely |
| Food groups and textures | Eats from most groups | Refuses whole textures or nutrition groups |
| Favorite foods | May tire of one, then return to it later | Often drops foods and does not return to them |
| Mealtimes | Occasional frustration | Frequent stress for child and family |
The framework in the table comes from the Feeding Matters comparison. Use it to start a conversation with your child's doctor, not to label your child at home.
What picky eating usually looks like
Picky eating is very common in toddlers and preschoolers, and it often comes with a growing sense of independence. Here is what we often hear from parents of picky eaters:
- "She loved bananas last month, now she won't touch them."
- "He'll eat the pasta but pushes the vegetables to the side of the plate."
- "She will take one bite if I ask, then say she's done."
Notice what these children have in common: they still have a decent variety, they can be around new foods without distress, and they usually come back to foods they paused. Growth stays on track, and mealtimes are annoying more than frightening.
What problem feeding can look like
Problem feeding is a pattern, not a single bad meal. These are the kinds of things parents describe to us:
- A short list of accepted foods that keeps getting shorter.
- Gagging, vomiting, or crying when certain foods are on the table or even nearby.
- Refusing an entire texture, such as anything crunchy or anything mixed, or an entire group, such as all fruits or all proteins.
- Eating only one brand or one presentation of a food.
- Meals that take very long, or that end in tears for everyone.
- A parent who has started cooking separate meals, bribing, or dreading dinner.
The cause is rarely stubbornness. A child may have a sensory sensitivity, oral-motor difficulty, reflux, constipation, a history of choking or tube feeding, or a learned fear of eating. Often it is a mix, which is why we look for root causes instead of quick fixes.
Red flags that mean it is time to call the doctor
Some signs go beyond how many foods your child eats. Feeding Matters lists possible signs of pediatric feeding disorder, including lack of energy, poor weight gain, dehydration, extreme picky eating, mealtime tantrums, and caregiver stress or feeling overwhelmed.
Its "When to Refer" materials add medical and feeding-skill triggers. These include labored breathing, color changes, recurring upper respiratory infections, vomiting, not eating or drinking enough to grow or stay hydrated, a need for thickened liquids or modified textures, and refusal of certain textures.
If you see breathing changes, color changes, repeated vomiting, or signs of dehydration, call your pediatrician promptly rather than waiting to see if it passes. If your child is under one year old and you are seeing feeding red flags, our guide to recognizing your baby's feeding red flags is a good place to start.
Persistent restriction can also affect more than nutrition. Children and teens with long-term food restriction can face oral health consequences too, which is one more reason to get a professional opinion early. This overview of dental complications of eating disorders shows how far-reaching food restriction can be for the mouth and teeth.
Where ARFID and pediatric feeding disorder fit in
Two more terms come up often, and they are worth understanding.
Pediatric feeding disorder (PFD) is a medical diagnosis term. Feeding Matters describes it as impaired oral intake that is not age-appropriate and is associated with medical, nutritional, feeding skill, and/or psychosocial dysfunction. The American Speech-Language-Hearing Association (ASHA) uses the same framing in its referral guidelines, which support screening by several professionals working together instead of one discipline alone. We go deeper in our article on what to do when feeding trouble lasts more than two weeks.
ARFID (avoidant/restrictive food intake disorder) is a recognized eating disorder in which a person severely limits food intake. UCLA Health notes that a key difference from ordinary pickiness is that the average picky eater is still hungry and wants to eat, while a child with ARFID may go all day without food even when hungry, because of the discomfort eating brings. It also says children with ARFID typically need medical help. Our own piece, ARFID vs. picky eating, explains how to tell them apart.
"Problem feeder" is a practical, everyday term. ARFID and PFD are formal diagnostic frameworks. A child can be a problem feeder without meeting criteria for ARFID, and only a qualified clinician can say which applies.

Why a picky eater can become a problem feeder
Most picky eaters never become problem feeders. But when pressure rises, things can shift. One common pattern: a child who is cautious about food meets a worried adult who coaxes, bargains, or insists on "just one bite." The child feels pushed, the table feels unsafe, and caution turns into fear.
A few things often feed that loop:
- Pressure. Pleading, bribing, and punishing. HealthyChildren.org, from the American Academy of Pediatrics, advises offering healthy foods, not forcing children to eat, and not using food as a reward or punishment, and notes that food rewards or bribes usually create more problems.
- Unaddressed physical causes. Reflux, constipation, allergies, or oral-motor weakness can make eating uncomfortable. A child who learns that eating hurts will understandably avoid it.
- Sensory sensitivity. Smell, texture, temperature, and even the look of a food can be overwhelming for some children.
- A shrinking diet. Each lost food makes the next meal harder, so the list narrows.
If you recognize pressure in your own home, take a breath. Nearly every loving parent has been there. Our article on easing pressure at meals offers gentle ways to reset.
What you can try at home
These steps are helpful for picky eaters and are a safe foundation while you wait for an evaluation with a problem feeder. They do not replace a medical visit if you see red flags.
- Rule out health causes first. Boys Town National Research Hospital advises a pediatric visit to rule out health causes before changing mealtime routines.
- Keep meals calm and predictable. Set regular meal and snack times, sit together, and keep the mood light. Boys Town recommends consistent meal rules and no nagging, pressure, or punishment at the table.
- Serve a safe food alongside new ones. Put one food your child reliably eats on the plate with a small portion of something new. No bites required.
- Let exposure count. Touching, smelling, or just seeing a food is progress. Our guide to low-pressure home steps for sensory food aversion shows how.
- Follow your child's cues. Our overview of responsive feeding principles helps you read hunger and fullness and respond with warmth.
- Keep food neutral. Skip dessert as a prize and "clean plate" rules.
A small example: a parent we might meet says her three-year-old cries whenever a vegetable touches her plate. We would start by shrinking the goal. Put a single green bean on a separate small plate, nobody mentions it, and everyone eats. Some days it is ignored. Some days it is poked. Those are real steps, and they add up when the table feels safe.
When to ask for a feeding evaluation
Consider reaching out when any of these are true:
- Your child accepts fewer than about 20 foods, or the list keeps shrinking.
- New foods cause crying, gagging, or complete refusal.
- Whole textures or food groups are gone.
- Your child is not growing as expected, or has low energy.
- Meals are stressful most days, for your child and for you.
- Your pediatrician has raised concerns.
Feeding Matters advises caregivers who are worried about the amount or type of food a child eats to contact the child's doctor, who may recommend a specialist evaluation, and you can ask for a referral. You can also reach out to us directly. To see what the process involves, read about what a child feeding evaluation looks like. A food diary and a short video of a typical meal help us find causes faster.
What feeding therapy involves
Feeding therapy is not a trick to make a child eat broccoli. According to ASHA, speech-language pathologists can help children suck from a bottle or drink from a cup, adjust food textures and liquid thickness for safe swallowing, try different positioning, chew, and accept new foods.
In practice, therapy usually blends several pieces:
- Understanding why eating is hard for your child, whether sensory, motor, medical, or behavioral.
- Gradual, playful exposure to foods at a pace your child can handle.
- Coaching for you, so mealtimes at home feel supportive.
- Coordination with your pediatrician and other providers when needed.
Want more detail? Our overview of pediatric feeding therapy and our article on how feeding therapy helps toddlers walk through what sessions are like.
Our perspective: look for the root cause
We have sat across from many parents who have been told, "He'll grow out of it," and many others who have been told, "Just make her eat it." Neither answer helps when you are the one standing at the table every night.
Our view is that the label matters less than the why. Whether a child is a picky eater, a problem feeder, or somewhere in between, we want to understand what is making eating hard: sensory sensitivity, oral-motor skills, medical factors, or the feedback loop that builds when meals become stressful.
That is why our approach is holistic and family-centered. We combine pediatric healthcare expertise with the lived experience of being a parent, and we focus on long-term change instead of quick fixes. Our therapists can work with your family in our office, at home, or at daycare or preschool, so support happens where your child actually eats.
You do not need to wait until things are severe. Early support can bring your child more confidence at meals and bring you more peace of mind.
Thriving Joy
Support from Thriving Joy
If mealtimes feel heavier than they should, we are here to help. Thriving Joy Pediatric Therapy offers feeding therapy for infants and children in Lutz and Wesley Chapel, serving families across Pasco and Hillsborough Counties. We also offer parent coaching, feeding support groups, and picky eating workshops for families who want practical tools. We accept private pay, major health insurance plans, and scholarships. Reach out through our website to ask about a first step.
FAQ
Is feeding therapy good for picky eaters?
It can be, especially when picky eating is starting to affect growth, variety, or family stress. Feeding therapy looks at why your child avoids certain foods and builds comfort step by step. Many picky eaters do well with simple home strategies, and a short consultation or parent workshop can be enough to get you started.
What is problem feeding?
Problem feeding is a pattern in which a child's eating is significantly limited, often to fewer than 20 foods, with strong distress or refusal around new foods or whole textures. It can have sensory, medical, motor, or behavioral causes. A feeding specialist can help sort out which are involved.
What's the difference between ARFID and picky eating?
ARFID is an eating disorder in which food intake is severely limited, and children with it typically need medical help. Picky eaters generally still feel hungry and want to eat. Only a clinician can diagnose ARFID, so bring your concerns to your pediatrician.
Can a picky eater turn into a problem feeder?
Sometimes, particularly when mealtimes become stressful or pressure builds. Calm routines, no forced bites, and early support when the diet shrinks can help prevent that path. If you are unsure, a feeding evaluation can give you clarity.
Should I wait to see if my child grows out of it?
If your child is growing well, eats a good variety, and can tolerate new foods nearby, patience is often reasonable. If you see red flags such as poor weight gain, breathing trouble with meals, or a shrinking list of foods, talk to your pediatrician sooner rather than later.
Sources
- Picky Eaters Versus Problem Feeders, Feeding Matters
- PFD FAQs, Feeding Matters
- When to Refer infographic, Feeding Matters
- Guidelines for Referring Patients to Speech-Language Pathology for Pediatric Feeding Disorder, ASHA
- Picky eating vs. ARFID, UCLA Health
- How to Handle Mealtime Struggles, HealthyChildren.org
- Parenting the Picky Eater, Boys Town National Research Hospital
- ASHA Shares Resources for Families on Feeding Development
- Dental complications of eating disorders
Recommended
- ARFID vs. Picky Eating: How to Tell the Difference
- Pediatric Feeding Disorder: After Two Weeks, Parents Need a Team
- Food Chaining for Picky Eaters: A Step-by-Step Guide
- Parents: 5 Low Pressure Home Steps for Sensory Food Aversion
The information provided in Finding Joy's blog articles is for educational and informational purposes only and is not intended as medical advice, diagnosis, or treatment. Content should not be used as a substitute for professional medical advice from a qualified healthcare provider. Always consult your physician or healthcare professional regarding any medical condition, symptoms, medications, or treatment options. Never disregard professional medical advice or delay seeking treatment because of