

Reflux is common in breastfed babies and usually improves with simple feeding and positioning changes, not medicine; to understand why reflux is common, see how the newborn digestive system works. Try smaller, more frequent feeds, keep your baby upright after nursing, and check your latch before you assume something is wrong. Call your pediatrician right away if you notice poor weight gain, blood in spit-up, forceful vomiting, or any trouble breathing.
TL;DR:
- Most infants outgrow normal reflux by around 12 months through simple feeding and positioning adjustments without medication.
- Signs of serious issues include projectile vomiting, green or bloody vomit, trouble breathing, or severe dehydration requiring immediate medical attention.
- Feeding slow, paced, and upright positioning helps reduce reflux symptoms, especially in babies with fast let-down milk flow.
- Maternal diet changes, like eliminating dairy, are rarely effective for ordinary reflux and should only be tried under medical supervision.
- Lactation consultants can identify mechanical feeding issues like latch or oversupply that might be mistaken for or contribute to reflux symptoms.
Table of Contents
- Reflux and Breastfeeding: Normal Spit-Up vs Warning Signs
- When to Seek Help for Reflux and Breastfeeding
- Breastfeeding Positions and Techniques That Ease Reflux
- Does Maternal Diet Cause Reflux in Breastfed Babies?
- Medical Treatments for Infant Reflux and Their Limits
- How a Lactation Consultant Helps With Reflux
- A Closing Perspective on Reflux and Breastfeeding
- Get Personalized Support for Reflux and Breastfeeding
- Sources
Reflux and Breastfeeding: Normal Spit-Up vs Warning Signs
Most babies who spit up are perfectly fine. At least 40% of infants have at least one daily episode of bringing up milk, and the overwhelming majority grow out of it by around 12 months. If your baby spits up happily, keeps gaining weight, and seems content between feeds, you're likely watching a normal, messy stage of infancy rather than a medical problem.
Typical, harmless reflux usually looks like this:
- Spit-up within an hour of feeding, often with a burp
- Baby seems unbothered afterward and continues to feed well
- Steady weight gain and normal wet diapers
- Occasional hiccups or small amounts of milk after burping
Silent reflux is trickier because there's little or no visible spit-up. Watch for back-arching during or after feeds, sudden feeding refusal, chronic coughing, or a raspy cry. Because nothing comes back up, parents often miss it or mistake it for colic.
Red flags that need same-day medical attention include forceful or projectile vomiting, vomit that's green, yellow, or bloody, and any sign of breathing difficulty during feeds.
When to Seek Help for Reflux and Breastfeeding
Not every worrying moment means an emergency room visit, but some do. Use this quick triage before you decide whether to call now, book a routine visit, or simply keep watching.
- Go now (call 911 or go to the ER): trouble breathing, blue lips, severe dehydration (no wet diaper in 6+ hours), bloody or bile-colored vomit, or inconsolable high-pitched crying.
- Call your pediatrician today: repeated projectile vomiting, refusal to feed for several hours, or noticeable lethargy.
- Bring it up at the next visit: slow weight gain, occasional feeding refusal, or reflux that seems to be getting worse rather than better after a few weeks.
Rare but serious conditions like pyloric stenosis can mimic reflux, which is exactly why persistent vomiting deserves a real exam rather than a guess. Before any appointment, jot down feeding times, how often spit-up happens, what it looks like, wet diaper counts, and recent weight if you know it. That log turns a vague "he's been fussy" into information your pediatrician can actually use, and it's worth reviewing our feeding red flags guide if you want a fuller checklist.
Breastfeeding Positions and Techniques That Ease Reflux
Feeding mechanics matter more than most parents expect. A baby who gulps down milk too fast swallows extra air, and that air has to come back up somehow, often bringing milk with it.
If you have a strong or fast let-down, try offering one breast per feed instead of switching sides, or start on the side that already released some milk into a cloth. This slows the flow so your baby swallows less air. Paced feeding, whether at the breast or with a bottle of expressed milk, gives babies more control over their own gulping.
Positioning helps too. Feed with baby's head higher than their stomach, keep them upright for 20 to 30 minutes after eating, and skip the car seat right after a feed when you can, since the semi-reclined position puts pressure on a full stomach. The NHS recommends exactly this combination of upright holding and smaller, more frequent feeds as a first response, and most babies improve simply by feeding more often at each sitting.
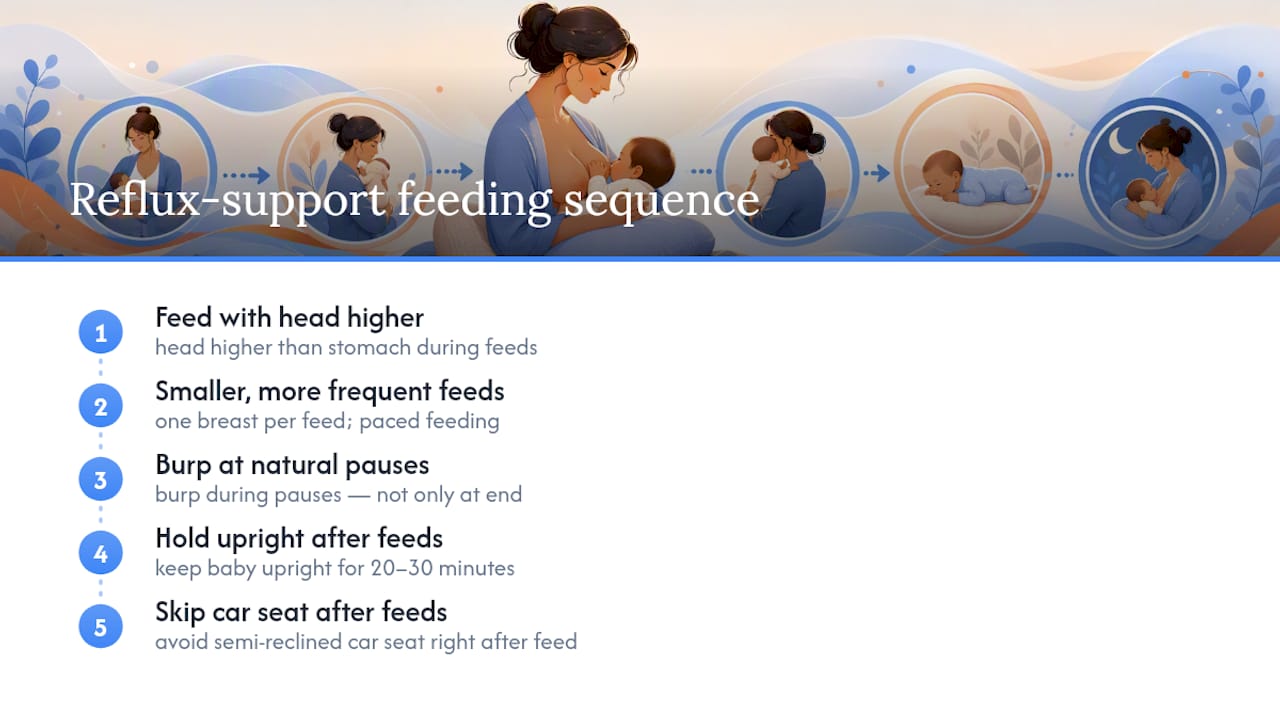
Burp gently at natural pauses rather than waiting until the end. Offering comfort sucking at an already-drained breast can also settle a fussy baby without adding more milk to an already full stomach.
A few environmental factors are worth checking, too. Secondhand smoke and high maternal caffeine intake have both been linked to worse reflux symptoms in some babies. And whatever positioning you use during the day, always return to safe, flat, back sleeping for naps and nighttime.
Pro Tip: If your baby gulps, coughs, or pulls off the breast repeatedly during let-down, try leaning back slightly while nursing. Gravity works against the fast flow instead of helping it.
Does Maternal Diet Cause Reflux in Breastfed Babies?
Cow's milk protein allergy (CMPA) can produce reflux-like symptoms, including vomiting, blood-streaked stool, or eczema, but it's uncommon in exclusively breastfed infants. Cutting dairy or other foods from your own diet without guidance rarely solves ordinary reflux and can leave you short on nutrients you need while nursing.
If your pediatrician suspects CMPA, a structured elimination trial typically looks like this:
- Remove dairy (and sometimes soy) from your diet for two to four weeks, tracking symptoms daily
- Watch specifically for improvement in vomiting, stool changes, or skin symptoms, not just fussiness
- Reintroduce the food under guidance to confirm the connection before committing to long-term restriction
- Work with your pediatrician or a dietitian rather than eliminating multiple food groups on your own
Unsupervised, overly restrictive diets can quietly undermine your energy and milk supply, so any trial worth doing is worth doing with someone tracking it alongside you.
Medical Treatments for Infant Reflux and Their Limits
Medicine is rarely the first answer, and for good reason. Clinical reviews describe a genuinely limited role for acid-suppressing drugs like H2 blockers and proton pump inhibitors in typical infant reflux. They're reserved for babies with diagnosed GERD, meaning reflux severe enough to cause poor growth, esophagitis, or feeding aversion, and they're used under specialist supervision.
- Alginate preparations can reduce visible spit-up in the short term but don't stop reflux itself, and they sometimes cause constipation, so clinicians trial them cautiously.
- Thickening feeds is common with formula but a Cochrane review found limited evidence it helps, and thickening breastmilk raises practical and safety concerns that make it far from routine for breastfed babies.
- Formula switching isn't relevant for exclusively breastfed infants and shouldn't be suggested as a fix for normal spit-up.
- Gripe water and simethicone have thin evidence behind them, and it's worth checking with your provider before relying on either one.
If reflux is severe, unresponsive to feeding changes, or paired with poor growth, your pediatrician may refer you to pediatric gastroenterology for further evaluation.
How a Lactation Consultant Helps With Reflux
An IBCLC looks at what medicine often can't see in a quick visit: the actual mechanics of a feed. That includes latch quality, milk flow, tongue mobility, swallows per minute, and whether oversupply is pushing too much milk too fast.
A typical consult includes:
- A full feeding observation, watching latch, positioning, and swallowing rhythm in real time
- Specific adjustments like block feeding, paced feeding, or repositioning to slow flow
- A follow-up plan to see whether symptoms ease within days, not months
Before your appointment, it helps to note feeding times, fussiness patterns, and anything that seems to trigger worse spit-up. Many families are surprised to learn that what looked like reflux was actually oversupply or a shallow latch, both of which respond well to hands-on support. If you want to understand what that assessment looks like in practice, our guide to certified lactation consultant support walks through it in more detail.
A Closing Perspective on Reflux and Breastfeeding
Most of this settles down on its own, and most parents figure that out the hard way, through months of laundry and worry before someone finally says "this is normal." You don't have to wait that long. Try the feeding and positioning changes first, track what you see, and trust your instincts on red flags. If things aren't improving after a couple of weeks of real effort, that's not failure. That's exactly when feeding or lactation support earns its keep.
— Jamie
Get Personalized Support for Reflux and Breastfeeding
A feeding log and a few positioning tweaks solve plenty of cases, but not all of them, and you shouldn't have to guess which category your baby falls into. Lactation counseling and pediatric feeding therapy are available from a clinic that provides a full evaluation of latch, flow, and feeding mechanics rather than a quick fix aimed at the symptom alone.
An initial consult typically includes a hands-on feeding observation, a review of your baby's growth and history, and a plan you can start using that same day. The team accepts most major insurance plans and works from a family-centered approach that looks for the root cause behind fussiness at the breast, not just the reflux label. If feeding changes haven't settled things after a couple of weeks, or you simply want an expert set of eyes on your baby's latch, you can book a lactation counseling consult in Lutz or learn more about our feeding therapy services to get started.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Reflux in infants - MedlinePlus
- Peer-reviewed article on infant reflux (PMC)
- Feed-thickener for infants below six months with gastro-oesophageal reflux — Cochrane
- Reflux and breastfeeding — NHS (Best Start in Life)